
Effects of Contrast Media on Renal Function Following Computed Tomography Before Transcatheter Aortic Valve Implantation
Introduction: Cardiac computed tomography angiography (CTA) is vital in the pre-procedural planning of transcatheter aortic valve implantation (TAVI), essential for procedural success. The Use of iodinated contrast agents raises concerns about adverse effects on renal function, particularly in patients with pre-existing chronic kidney disease (CKD). These concerns are often cited as a reason to avoid this crucial test.
Objective: To study the real-world impact of CTA on renal functions.
Methods: This was a retrospective cohort of patients who underwent CTA before TAVI. Dialysis patients were excluded. Primary endpoints were AKI and new dialysis treatment.
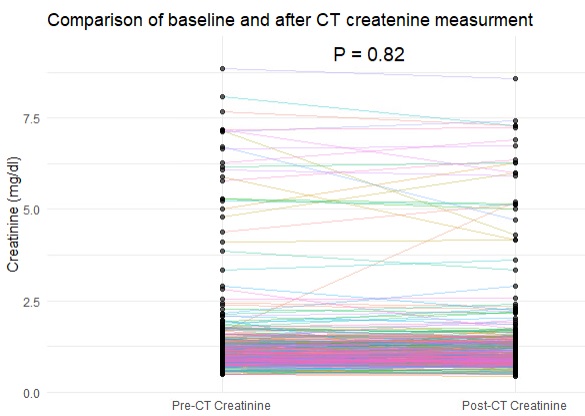
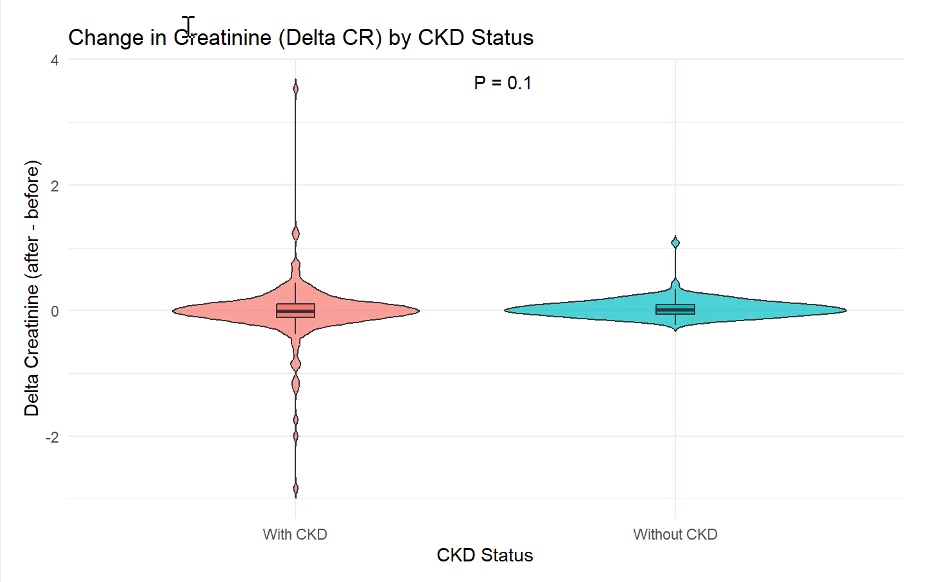
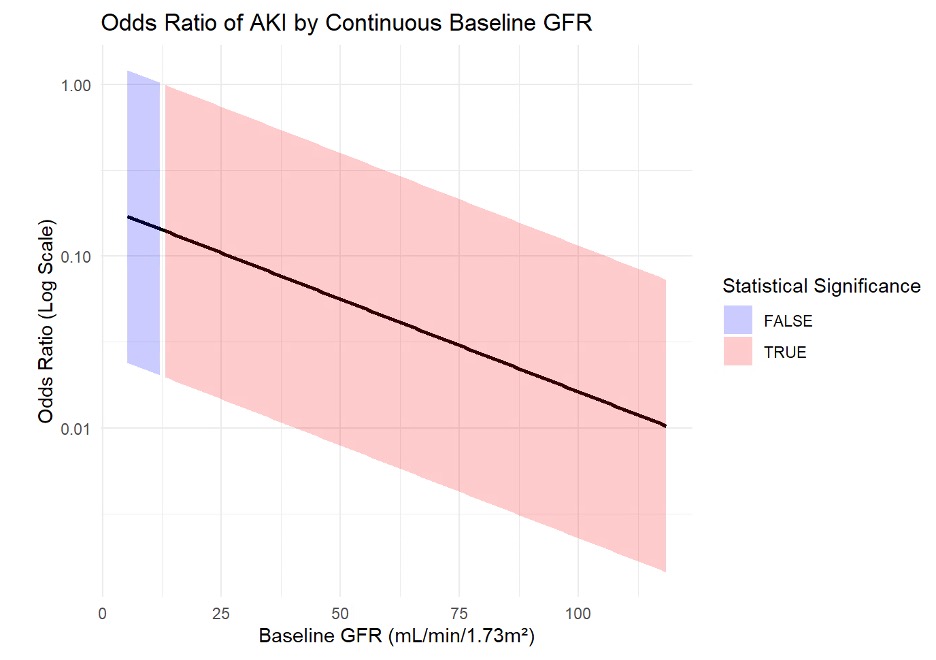
Results: The study cohort included 347 consecutive patients. The median age was 81, 46% were males. 203 patients (59%) had baseline CKD, and the median glomerular filtration rate (GFR) in the entire cohort was 56 ml/min/1.732. Patients with CKD were older but otherwise balanced for sex and comorbidities. There was no significant difference between baseline creatinine and the first creatinine after CTA (P = 0.82, Figure 1); which didn`t differ between patients with and without CKD (P = 0.1, Figure 2). Acute Kidney Injury (AKI) occurred only in 18 patients (5.2%). Baseline CKD predisposed AKI with an OR of 3.75 (CI 1.21-16.4, P = 0.04), but this was not significant after accounting for age and sex (p = 0.064). Most AKI events (61%) resolved during two sequential creatinine tests, and within 30 days of the CTA, no patients required dialysis. No correlation existed between the amount of contrast injected and follow-up creatinine (R = 0.09, P = 0.086). Increased GFR was negatively associated with AKI. GFR of more than 12.5 ml/min/1.732 is significantly associated with lower rates of AKI.
Conclusions: In patients undergoing CTA before TAVI, the occurrence of AKI is relatively uncommon. Performing CTA before TAVI is justified despite the high-risk profile in this population.
israelheart@ortra.com מייל לשאלות
