
Relation of Serum Creatinine Twitches and Outcomes among STEMI Patients
Background: From a wide array of in-hospital compilations, acute kidney injury (AKI) is notoriously associated with adverse outcomes and mortality in many acute conditions and in acute coronary syndrome patients in particular. However, using the general cutoff of 0.3 mg/dL increase from baseline for AKI definition and neglecting smaller changes could result in late diagnosis and impaired prognostication. Therefore, early reports evaluated the use of minor creatinine changes, that do not meet formal criteria, as a marker for adverse outcomes. We aimed to assess the prognostic utility of minor creatinine changes ("twitches") in a large cohort of STEMI patients and identify a more specific cutoff for future use.
Methods: This retrospective analysis of a prospective database included 2933 consecutive patients admitted with STEMI between 2008-2022 to the cardiac intensive care unit. Renal function was assessed upon admission and at-least once daily thereafter. Creatinine twitches were defined as a change from baseline to peak creatinine level of between 0.1 to 0.3 mg/dl. 30-day and 1-year mortality were the main outcomes.
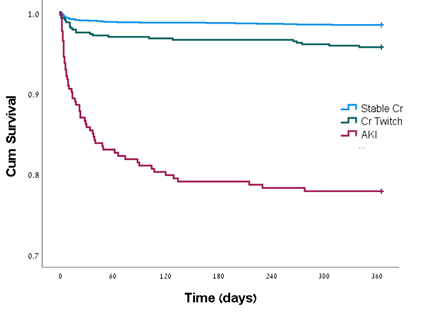
Results: From the study cohort, 551 (19%) subjects presented creatinine twitches and 254 (9%) developed AKI. Compared to subjects with stable creatinine, those with creatinine twitches had higher rates of 30-day (1% vs. 2.5%,p<0.001) and 1-year (1.6% vs. 4.4%, p<0.001) mortality. In cox multivariate analysis, creatinine twitches had a higher hazard for 1-year mortality compared with stable creatinine (HR 1.87, 95% CI 1.1-3.2). The optimal in-hospital increase in creatinine to predict 1-year mortality was 0.12 mg/dl, yielding 71% sensitivity and 79% specificity.
Conclusion: Serum creatinine twitches are common among STEMI patients and correlate with elevated 30 days and 1-year mortality. These seemingly minor changes should prompt renal protective strategies for early detection and treatment.
israelheart@ortra.com מייל לשאלות
