
Exploring Kidney functions as a key barrier to effective diuresis in Congestion Refractory Heart Failure: Insights from the DEA-HF Clinical Trial
2Ruth and Bruce Rappaport Faculty of Medicine, Technion, Israel
3Clinical Research Institute at Rambam (CRIR), Rambam Health Care Campus, Israel
Introduction: Kidney dysfunction hinders effective decongestion in chronic heart failure (HF). Diuretic efficacy depends on HF severity, glomerular filtration rate (GFR), acid-base balance, diuretic type, dosage, and treatment duration. Patients with chronic HF and volume overload despite guideline-directed medical therapy and optimized oral diuretic therapy, pose a significant clinical challenge. This study uniquely focuses on the comparative evaluation of three distinct diuretic regimens, examining how estimated GFR (eGFR) and serum bicarbonate levels influence their efficacy in this congestion-refractory patient population.
Method: Retrospective data analysis from the prospective, randomized, cross-over DEA-HF trial. Forty-two patients received weekly one of three high-intensity diuretics, in a randomized order: IV furosemide 250mg; oral metolazone 5mg+IV furosemide 250mg; and IV acetazolamide 500mg+IV furosemide 250mg. Efficacy was evaluated by total sodium excretion and urine volume.
Results: All diuretic regimens demonstrated a consistent pattern, with natriuresis efficacy correlating with eGFR. A single diuretic session (regimen-independent) resulted in significantly higher natriuresis in patients with higher eGFR: estimated mean Sodium exertion of 5593mg (95% CI:4929-6257) in patients with eGFR>45ml/min/1.73m2 compared to 4929mg (95% CI:3694-4891, P<0.01) in eGFR 30-45ml/min/1.73m2 and 2934mg (95% CI:2345-3522, P<0.001) in eGFR<30ml/min/1.73m2. Urine volume followed a similar trend. Nevertheless, patients in all eGFR groups achieved statistically comparable significant reductions in body weight, serum NT-ProBNP, congestion score, and lung ultrasound B-lines. Regardless of the diuretic regimen, higher baseline bicarbonate levels were associated with a greater diuretic effect. Worsening of renal function was more common with eGFR<30ml/min/1.73m² (12%) than in eGFR 30-45(7.7%) or >45(6.3%), without associated HF or renal-related admissions.
Conclusions: Natriuresis and diuresis efficacy in patients with congestion-refractory chronic HF were positively associated with higher eGFR and serum bicarbonate levels, irrespective of the diuretic regimen used. Although natriuresis effectiveness demonstrated a clear dependence on eGFR, all eGFR groups achieved decongestion with diuretic therapy.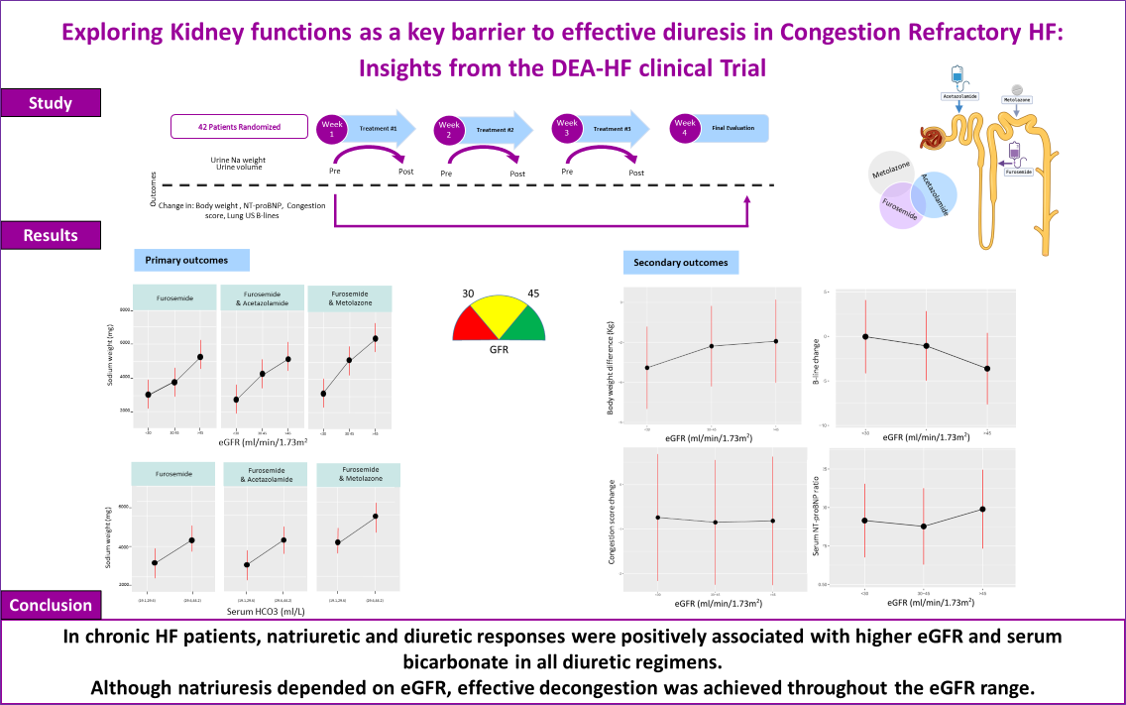
israelheart@ortra.com מייל לשאלות
